


Breast Augmentation (Augmentation Mammoplasty) Sydney
Breast augmentation, also called augmentation mammoplasty, is a surgical procedure that may increase breast volume and adjust breast shape using implants and, in selected cases, fat transfer. It is usually performed under general anaesthesia in an accredited hospital or surgical facility. Surgical time varies based on individual anatomy, implant type and size, incision location, implant placement, and whether other procedures are performed at the same time. Some patients return home the same day, while others stay overnight, depending on clinical factors and the treating team’s plan.
At Australia Cosmetic Clinics in Sydney, Dr Anthony Barker is a Specialist Plastic and Reconstructive Surgeon whose practice includes breast reconstruction and enhancement. His background in medicine and biomedical engineering informs his approach to anatomy, structure and individualised surgical planning. Breast augmentation consultation focuses on clarifying the patient’s priorities, assessing breast and chest anatomy, and discussing implant options, incision and pocket choices, expected recovery, and potential risks. Incisions are required for implant placement and scars are expected, with scar location determined by the incision approach and individual planning.
All photographs have been used with the patient’s express written permission. The information on this site is not intended to replace expert medical advice. There are risks associated with any surgical or invasive operation. You should obtain the advice of a licensed health professional before continuing.
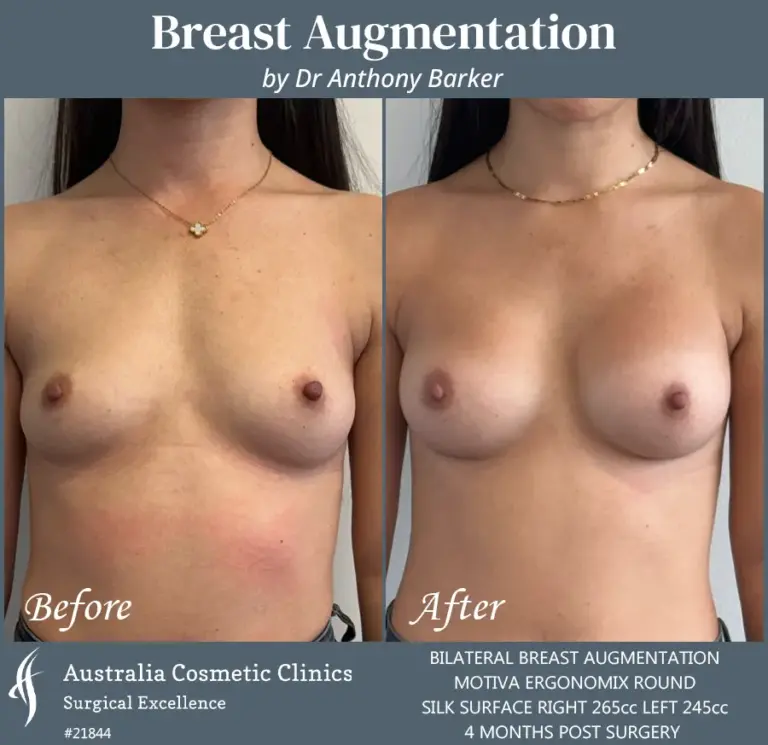
What is Breast Augmentation (Augmentation Mammoplasty)?
Breast augmentation is a procedure that places an implant to change breast volume and, in some cases, breast shape. The implant is inserted into a pocket created during surgery. Pocket position may be under the breast tissue, under the pectoral muscle, or in a dual plane position that uses elements of both locations depending on the plan. Breast augmentation is not a single technique. It is a category of procedures with multiple variables, including implant dimensions, implant projection, implant surface type, incision placement, and pocket location.
A common misconception is that implant volume alone determines the result. Planning commonly prioritises implant base width relative to chest width, as well as tissue thickness and skin elasticity. Patients with limited tissue coverage may be more likely to notice implant edges or rippling, particularly with larger implants. These factors are discussed during consultation to support safe planning and realistic expectations.
Breast augmentation does not stop natural changes related to ageing, pregnancy, breastfeeding, hormonal influences, or weight change. It also cannot eliminate natural asymmetry entirely. These limitations form part of the consent discussion.
Pocket position options may include:
- Under breast tissue
- Under pectoral muscle
- Dual plane positioning
Planning variables include:
- Implant base width and projection
- Tissue thickness and skin elasticity
- Incision location and pocket design
- Existing asymmetry and chest wall differences

Why Do People Enquire About Breast Augmentation?
Breast augmentation is one of the more commonly performed breast procedures. Patients enquire for different reasons. For some, the priority relates primarily to breast size. For others, the goal is to address differences between breasts in volume or shape, or to manage volume changes that occur after pregnancy, breastfeeding, or weight fluctuations. Some people focus on how clothing fits and how breast proportions relate to their overall frame.
Breast size and shape are influenced by genetics, glandular tissue volume, fat distribution, connective tissue support, and skin elasticity. These factors vary between individuals and can change over time. Exercise and general conditioning support overall health, but do not reliably change breast volume or breast position for many people, which is why surgical options may be explored.
Common reasons for enquiry include:
- Desire for increased breast volume
- Noticeable asymmetry between breasts
- Volume changes after pregnancy, breastfeeding, or weight change
- Preference for different proportions in clothing
- Interest in implant based augmentation or selected fat transfer discussion
What Is The Difference Between Implant-Based Augmentation And Fat Transfer?
Most breast augmentation procedures are implant-based. In selected cases, fat transfer may also be discussed. Implant-based augmentation uses a medical device to change volume and shape, while fat transfer uses the patient’s own tissue and may be limited by donor fat availability and graft take variability. Consultation is used to assess whether fat transfer is a realistic option in the individual’s circumstances and whether implant augmentation is more appropriate for the desired volume change.
When implants are used, discussion includes implant dimensions, projection, and how implant size interacts with breast base width and chest anatomy. The treating surgeon explains the trade-offs of different approaches, including how tissue coverage can influence implant edge visibility and the likelihood of rippling.
Implant-based augmentation discussion commonly includes:
- Implant dimensions and projection
- Incision options and scar locations
- Pocket position and tissue coverage
Breast fat transfer discussion may include:
- Whether donor fat is available
- The likely range of achievable volume change
- The variability of fat graft retention
Take our Plastic Surgery Quiz
How Is Suitability For Breast Augmentation Assessed?
Suitability for breast augmentation is determined through consultation with a qualified surgeon. This process reviews medical factors and whether the procedure aligns with the patient’s expectations. The treating surgeon reviews overall health, medical history, current conditions that may affect anaesthesia or wound healing, and any prior breast procedures. Allergies and previous anaesthetic issues are discussed. Family history and breast health history may also be reviewed where relevant.
Medication and supplement use is reviewed because some substances can increase bleeding risk or affect recovery. Smoking or nicotine exposure is an important part of assessment because nicotine reduces blood flow and increases the risk of wound healing problems and infection. Patients are commonly advised to stop smoking and avoid nicotine for a period before and after surgery, with requirements outlined by the treating surgeon.
Anatomy assessment is central to planning. The surgeon assesses breast base width, chest wall shape, tissue thickness, skin elasticity, breast position, nipple position, and degree of asymmetry. Weight stability is discussed because weight changes can influence breast size and shape. Future pregnancy and breastfeeding considerations are discussed because pregnancy can change breast volume and skin elasticity, and breastfeeding capacity after breast augmentation varies and cannot be predicted with certainty for every patient.
Consultation commonly reviews:
- Overall health, medical conditions, and surgical history
- Medications, supplements, and bleeding risk considerations
- Nicotine exposure and cessation requirements
- Breast health history and screening where relevant
- Breast and chest measurements and tissue assessment
- Weight stability and pregnancy planning
- Expectations, limitations, and risk discussion
Patients seeking cosmetic breast augmentation require a referral from an independent Australian-registered GP or other eligible medical specialist before consultation. Cosmetic surgery also requires at least two pre-operative consultations, including at least one in-person consultation with the surgeon performing the procedure. Following informed consent, a minimum seven-day cooling-off period applies before surgery can be booked or a deposit paid.
What Factors Influence Breast Implant Choice?
Implant selection is guided by anatomy and the agreed plan. Implant base width relative to chest width is often a key planning factor. Tissue thickness influences the degree of implant coverage and can affect whether implant edges may be visible or palpable. Skin elasticity and existing breast position influence how the implant may settle over time. These considerations are discussed to support safe planning and realistic expectations.
Sizing discussions are usually framed as a range rather than a single number. Bra cup size is not a reliable surgical measurement because sizing varies between brands and styles. For this reason, consultation focuses on measurements, proportions, and implant dimensions rather than a guaranteed cup size outcome.
Implant selection commonly considers:
- Base width relative to chest width
- Projection and overall proportions
- Tissue thickness and edge coverage
- Skin elasticity and breast envelope characteristics
- Existing asymmetry and chest wall differences
Sizing discussions commonly include:
- A measurement based planning approach
- A range of suitable implant options
- A discussion of trade offs related to larger implants
What Should You Know About Incision Options and Scar Locations?
Incisions are required to place implants, and scars are expected. Scar location depends on the incision approach selected and the patient’s anatomy and surgical plan. Common incision locations include the inframammary fold, placed in the crease under the breast, a periareolar incision around the border of the areola in selected cases, and an axillary incision in the underarm in selected cases. The treating surgeon explains why a particular incision may be recommended and what scar placement is likely.
Scar appearance varies between individuals and changes over time during scar maturation. Factors that influence scar quality can include genetics, skin type, tension on the incision, aftercare, and nicotine exposure. Follow-up appointments allow the treating team to monitor healing and provide scar care guidance when appropriate.
Common incision options include:
- Inframammary fold incision
- Periareolar incision in selected cases
- Axillary incision in selected cases
Scar expectations include:
- Scars are permanent but typically change in appearance over time
- Scar placement depends on approach and anatomy
- Scar care may be discussed once incisions are sealed and stable
Where Can Breast Implants Be Positioned?
Implants may be placed under the breast tissue, under the pectoral muscle, or in a dual plane position. The choice depends on tissue thickness, chest wall anatomy, implant type, and surgical goals. Pocket creation is performed carefully to support implant position and symmetry. Perfect symmetry is not always achievable because chest wall and breast differences are common, but planning aims to reduce noticeable differences.
The treating surgeon explains trade-offs of different placement options, including how placement may influence implant edge visibility, movement with muscle activation, and long-term support. The best approach varies, so placement decisions are made using a combination of anatomy assessment and the patient’s goals.
Pocket position decisions consider:
- Tissue thickness and implant coverage needs
- Chest wall anatomy and muscle characteristics
- Implant dimensions and intended proportions
- The extent of asymmetry and how it is approached in planning
How Is Breast Augmentation Performed, And What Happens In Hospital?
Breast augmentation is performed under general anaesthesia in an accredited hospital or surgical facility. The technique is tailored to anatomy and the agreed plan. The procedure typically involves implant selection confirmation, incision placement, pocket creation, implant insertion, and layered closure. Dressings are applied after closure and a supportive bra may be fitted. Some surgeons use drains in selected cases depending on technique and intraoperative findings.
Preoperative preparation is tailored to the patient’s health profile. Instructions may include fasting before anaesthesia, medication adjustments where clinically appropriate, nicotine avoidance, and planning for recovery at home. Practical preparation often includes organising transport home, arranging a support person for the first night if discharged the same day, and planning time away from work.
After surgery, patients are monitored in recovery. Discharge timing depends on recovery from anaesthesia, pain control, nausea control, and clinical assessment. Some patients go home the same day and others stay overnight depending on clinical factors and the treating team’s plan.
The pathway commonly includes:
- Pre-operative assessment and planning
- Surgical markings before theatre
- General anaesthesia and monitoring
- Implant insertion and layered closure
- Dressings and supportive garment fitting
- Recovery monitoring and discharge planning
Home preparation may include:
- Transport and a support person for early recovery
- A recovery area with easy access to supplies
- Planning time away from work and modifications to tasks
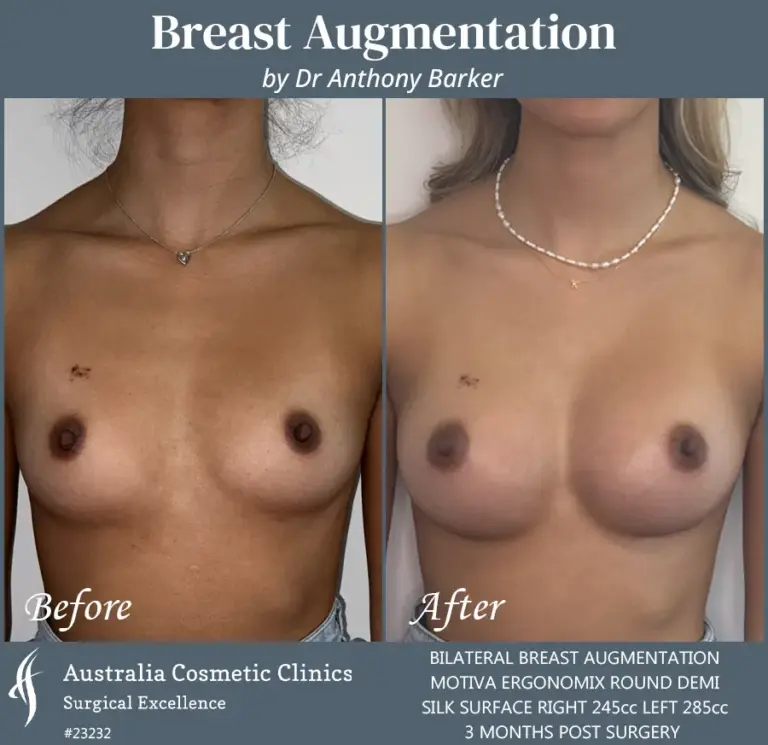
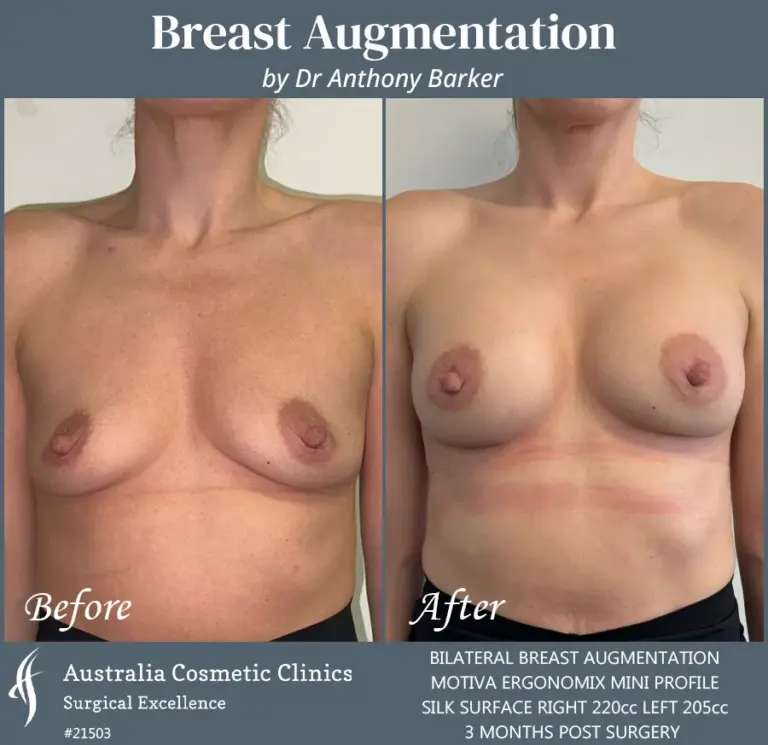
Breast Augmentation Before & After Photos
View Breast Augmentation Before and After Photos
Disclaimer
All photographs have been used with the patient’s express written permission. The information on this site is not intended to replace expert medical advice. There are risks associated with any surgical or invasive operation. You should obtain the advice of a licensed health professional before continuing.
What Recovery and Follow-Up Care Guidelines Should You Remember?
Recovery after breast augmentation is gradual and varies between individuals. The treating surgeon’s post-operative instructions take priority because they are tailored to technique and healing progress. Follow-up appointments are used to monitor wounds, swelling, and early implant position. Early changes may be visible soon after surgery, while swelling reduction and scar maturation may take months. Final breast appearance can continue to change over time as tissues settle.
In the first days to two weeks, swelling, bruising, and tightness across the chest are common. Variable discomfort is expected and is managed with prescribed or recommended medication. Tiredness is also common after anaesthesia and during early healing. Patients are often advised to avoid heavy lifting and repetitive overhead movement early, while light walking is commonly encouraged as advised to support circulation.
Time away from work depends on the physical requirements of the role. Some patients return to desk-based work after a shorter period, while physically demanding roles require longer modification. Driving is usually considered once the patient can safely perform an emergency stop and is no longer using medication that may impair reaction time.
Activity is reintroduced in stages. Walking is usually appropriate early, while higher intensity exercise is delayed until healing is progressing well. Upper-body strength training and high-impact activity are commonly delayed longer than lower-intensity movement. Timing depends on wound healing, swelling reduction, implant position, the extent of pocket dissection, baseline conditioning, and exercise type.
Common early experiences may include:
- Swelling and bruising
- Tightness across the chest
- Variable discomfort
- Temporary changes in nipple or breast sensation
Follow-up care supports:
- Wound review and dressing guidance
- Monitoring of swelling and settling
- Activity progression advice
- Scar care discussion when appropriate
How Are Breast Augmentation Scars Managed, And Can Sensation Change?
Scars are permanent and change in appearance over time. Scar appearance varies and depends on factors such as genetics, skin type, wound tension, aftercare, and nicotine exposure. Scar management may include silicone-based products and sun protection, introduced after incisions have sealed and when advised by the treating surgeon. Some patients are also advised about scar massage at an appropriate stage depending on healing.
Temporary changes in nipple and breast sensation are common. Some patients experience areas of reduced sensation or altered sensitivity as swelling settles and nerves recover. Longer-lasting sensation changes are possible and are discussed during consultation and consent.
Scar care discussions may include:
- Expected stages of scar maturation
- When silicone-based products may be introduced
- Sun protection measures once appropriate
Sensation discussions commonly include:
- Temporary changes during early healing
- Variability in recovery over time
- The possibility of longer-lasting changes
When Should You Seek a Medical Review?
Patients are advised to seek prompt medical advice if symptoms suggest infection, bleeding, or other complications. If uncertain whether a symptom is expected, contacting the treating team is appropriate, because early review can clarify what requires assessment.
Seek prompt medical advice for symptoms such as:
- Increasing redness, warmth, swelling, discharge, or fever
- Sudden one sided swelling or significant bleeding through dressings
- Shortness of breath or chest pain
- Calf swelling or calf pain
What Should You Know About Breast Augmentation Results Over The Longer Term?
Results vary between individuals. Early after surgery, swelling and tightness can influence appearance. Over time, swelling generally reduces and implant position can settle as tissues adapt. Common changes during the settling period may include a gradual shift from a higher early implant position to a more settled position, softening of the breast over time, and scar colour and texture changes as scars mature. The timeframe varies between individuals.
Longer term, breast shape can change due to weight fluctuations, pregnancy and breastfeeding, natural ageing of skin and tissue, and changes in physical activity and muscle development. Breast implants are medical devices and may not last a lifetime. Future surgery may be required for reasons such as implant ageing, capsular contracture, rupture, changes in breast tissue over time, or patient preference. Monitoring and review form part of longer-term care.
Longer term considerations include:
- Ongoing changes to breast tissue over time
- The possibility of future revision surgery
- The need for review if new symptoms develop
- Implant ageing and device-related changes
How Much Does Breast Augmentation Cost In Sydney?
The cost of breast augmentation varies because the procedure is tailored to the individual. A consultation is required to determine the surgical plan and provide a detailed quote. Factors that may influence overall cost include surgical complexity, hospital or day surgery facility fees, anaesthesia fees, surgeon’s fees, implant device costs, post-operative garments where required, and post-operative care and follow-up as outlined by the clinic. A standard price cannot be provided without consultation, and a personalised quote is provided after assessment.
If a patient is exploring any rebate pathways, eligibility depends on clinical documentation and applicable criteria. This is assessed on an individual basis and clinic staff can explain what information is required for assessment.
Cost factors may include:
- Hospital and theatre fees
- Anaesthesia fees
- Surgeon’s fees
- Implant device costs
- Post-operative garments and dressings
- Follow-up care pathway
What Breast Augmentation Risks and Potential Complications Should You Be Aware Of?
All surgical procedures carry risks. A detailed discussion of risks and expected recovery is part of consultation and consent. The likelihood of complications varies depending on health, nicotine exposure, surgical complexity, and tissue characteristics. Potential risks include general surgical and anaesthetic risks such as infection, bleeding, delayed wound healing, fluid collection, scarring variation, and uncommon but serious risks such as blood clots.
Breast augmentation also involves implant-specific considerations. These may include capsular contracture, implant malposition, implant rupture or deflation depending on implant type, rippling or visible implant edges when tissue coverage is limited, nipple or breast sensation changes, breast discomfort that persists longer than expected in some cases, asymmetry, and the possibility of future revisional surgery. The treating surgeon explains how these risks apply to the individual and discusses risk reduction strategies.
Potential risks and complications may include:
- Infection and bleeding
- Delayed wound healing and scarring variation
- Fluid collection
- Anaesthesia-related risks and blood clots
- Capsular contracture
- Implant malposition
- Implant rupture or deflation depending on implant type
- Rippling or visible implant edges in some cases
- Sensation changes and asymmetry
- Possibility of revision surgery
About Dr Anthony Barker
At Australia Cosmetic Clinics in Sydney, Dr Anthony Barker is a Specialist Plastic and Reconstructive Surgeon whose practice includes breast reconstruction and enhancement, body contouring, post-pregnancy restoration and complex surgery following significant weight loss. His background combines medicine and biomedical engineering, with a BA in Biomedical Engineering from Harvard University, medical and surgical qualifications from the University of Sydney, and Fellowship of the Royal Australasian College of Surgeons in Plastic Surgery. His medical and engineering background informs his approach to anatomy, structure, function and individualised surgical planning.
Dr Barker also holds a senior clinical lecturer appointment at Macquarie University, where he mentors surgical trainees and contributes to research, including projects relating to breast implant safety and techniques in breast augmentation and reconstruction. He also provides reconstructive services to rural and Indigenous communities, including Broken Hill and the South Coast, and works closely with general practitioners to support continuity of care. At Australia Cosmetic Clinics, consultation provides an opportunity to discuss concerns, undergo clinical assessment, and receive individualised information about surgical options, limitations, recovery and potential risks.
- Specialist Plastic and Reconstructive Surgeon
- BA in Biomedical Engineering, Harvard University
- Bachelor of Medicine & Bachelor of Surgery, University of Sydney
- Master of Surgery (Plastics), University of Sydney
- Fellow of the Royal Australasian College of Surgeons (Plastic Surgery)
- Member of the Australian Society of Plastic Surgeons
- Member of the Australian Society of Aesthetic Plastic Surgeons
- Member of the American Society of Plastic Surgeons
- Senior Clinical Lecturer at Macquarie University
- Academic work includes breast implant safety and breast augmentation and reconstruction research


FAQs about Breast Augmentation (Augmentation Mammoplasty)
How long does breast augmentation surgery take?
Surgical time varies depending on implant selection, incision choice, pocket position, and whether additional steps are required to manage asymmetry. An estimate is provided after assessment.
Is breast augmentation performed under general anaesthesia?
General anaesthesia is commonly used. The anaesthetist discusses relevant risks and how discomfort and nausea are managed after surgery.
Where are scars located after breast augmentation?
Incisions are required and scars are expected. Common locations include the breast crease, around the areola in selected cases, or the underarm in selected cases.
How is implant size chosen?
Implant selection is based on measurements such as base width and tissue thickness, along with preferences about proportions. Cup size is discussed but is not a precise surgical measurement.
What is the difference between implants under tissue and under muscle?
Placement may be under the breast tissue, under the pectoral muscle, or dual plane. The best option depends on anatomy, tissue thickness, implant type, and surgical goals.
When can work and exercise be resumed?
Return to work depends on job demands, and return to exercise is staged. Walking is often introduced early as advised, while higher intensity activity is delayed until healing is progressing well.
Do implants last a lifetime?
Implants are medical devices and may not last a lifetime. Some patients require revision surgery in the future due to device changes, capsular contracture, rupture, malposition, or preference changes.
Medical References
- Evidence-based Clinical Practice Guideline: Reduction Mammaplasty / ASPS / https://www.plasticsurgery.org/documents/Health-Policy/Guidelines/guideline-2011-reduction-mammaplasty.pdf
- Breast Reduction / StatPearls – NCBI Bookshelf / https://www.ncbi.nlm.nih.gov/books/NBK441974/
- A systematic review of patient reported outcome measures for women with macromastia who have undergone breast reduction surgery / PMC – NIH / https://pmc.ncbi.nlm.nih.gov/articles/PMC6722998/
- Secondary reduction mammaplasty techniques and outcomes / PubMed – NIH / https://pubmed.ncbi.nlm.nih.gov/39151285/
Schedule a Breast Augmentation Consultation With Dr Barker
Patients considering breast augmentation can arrange a consultation at Australia Cosmetic Clinics with Dr Anthony Barker, Specialist Plastic and Reconstructive Surgeon. Consultation allows discussion of individual goals, clinical assessment of suitability, explanation of implant options and incision choices, and clear information about recovery planning, limitations and potential risks.
Enquiries and consultation requests can be made via the Australia Cosmetic Clinics website or phone. Patients may be asked to provide medical history details, a medication list, and relevant breast screening information where applicable.
Further Reading About Breast Augmentation
Breast Lift Surgery
Procedure Page
Fat Transfer to Breasts
Procedure Page
Breast Re-implantation
Procedure Page
Breast Implant Profiles
Implant Guide

What's Next?
Whether you are ready for a professional evaluation or just have a quick question, we’ve made it easy to connect with our team. Choose the option that best fits your needs below.
Book your Consultation
Take the first step toward your goals by filling out the brief form below. This information helps us understand your specific needs so we can make the most of our time together during your session. Once you submit your details, a member of our team will review your request and reach out shortly to confirm your appointment.
Patient Photo Assesment
Sending photos for a patient photo assesment can help you and your plastic surgeon prepare for your consultation. By reviewing clear, accurate photos, Dr Kohout can provide preliminary patient photo assessment like insights, assess your needs, and determine the right approach for your procedure.
Tips for Uploading Photos
ASK A FRIEND
Friend takes photo
GOOD LIGHTING
Plain wall, bright light
ALL ANGLES
Front / sides/ 45°
CLEAR & SHARP
No portrait mode
SEND ORIGINALS
No edits or compression
Specialist Plastic &
Reconstructive Surgeon
Registration: MED 0001192942
Dr Anthony Barker is a specialist plastic and reconstructive surgeon whose medical and engineering background shapes his approach to surgery. He integrates the precision of engineering with the artistry of plastic surgery, striving to balance aesthetics and function in every procedure. His practice spans breast reconstruction and enhancement, body contouring, post-pregnancy restoration and complex surgeries after significant weight loss. Recognised for his compassionate consultations, he customises each procedure to help patients achieve natural, confidence-boosting results using advanced techniques and technologies.
Qualifications & Professional Memberships
- BA in Biomedical Engineering (Harvard University)
- Bachelor of Medicine & Bachelor of Surgery (University of Sydney)
- Master of Surgery (Plastics – University of Sydney)
- Fellow of the Royal Australasian College of Surgeons (Plastic Surgery)
- Member – Australian Society of Plastic Surgeons, Australian Society of Aesthetic Plastic Surgeons, American Society of Plastic Surgeons



Accreditations



